
MSO vs IPA vs CIN: Comparing Ways to Gain Scale Without Selling Ownership
Three ways an independent practice gains scale and negotiating power without selling its ownership. Here is how the models differ.
Why Choose Us?

No Hidden Fees

No Surprise Pricing

Real Support from People Who Know Medical Billing
MSO, IPA, or CIN: Choosing the Right Path to Practice Growth
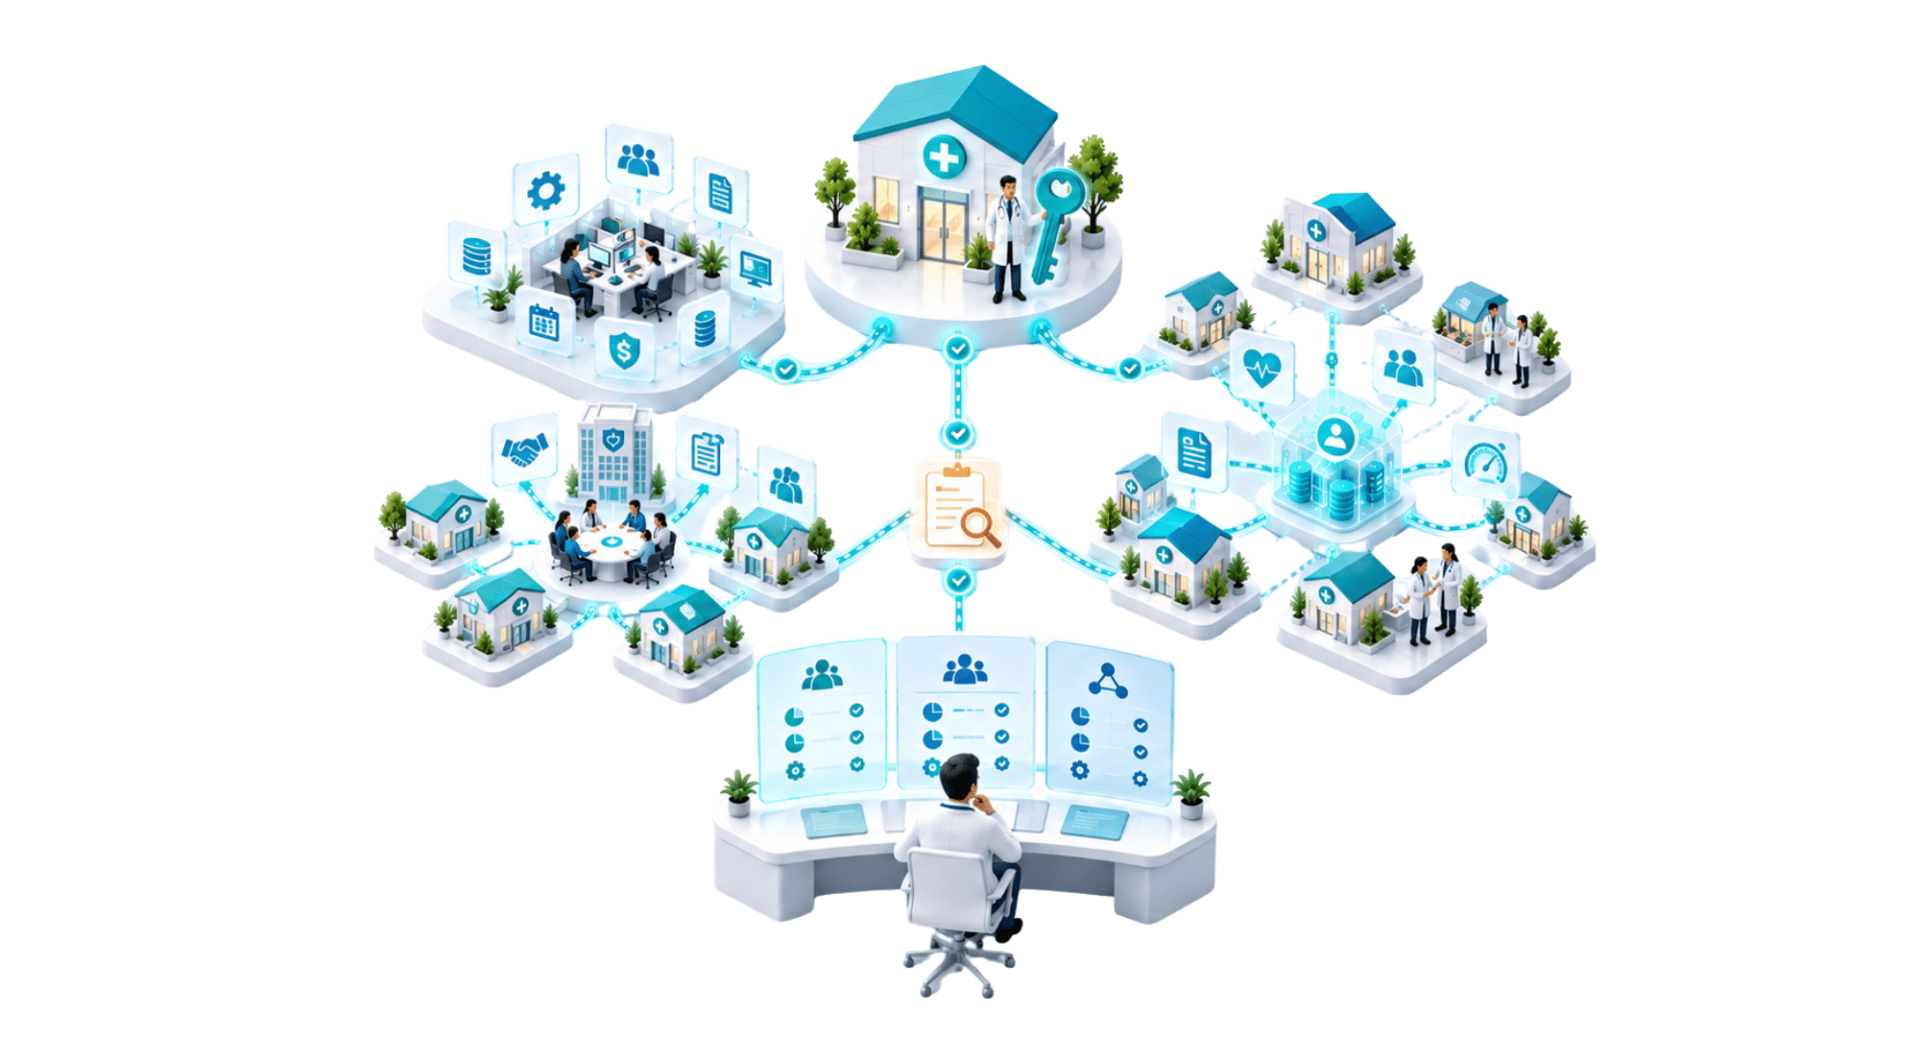
An owner looking past solo operation usually runs into three structures before a sale ever comes up: the management services organization, the independent practice association, and the clinically integrated network. Each lets a practice keep its ownership while gaining scale in one specific area, administrative operations, payer contracting, or clinical coordination, rather than trading equity for size the way an outright sale does.
The pull toward one of these structures is the same pull covered elsewhere in this cluster. 70.8 percent of physicians who left private practice named stronger payer rate negotiation as a top reason, 64.9 percent named access to costly resources, and 63.6 percent named the weight of regulatory and administrative work, according to the American Medical Association. Each structure below answers a different piece of this list.
This guide compares what each model changes about ownership and governance, what it typically costs, the regulatory shift behind joint payer negotiation, and how an owner decides which model, if any, fits a practice wanting to stay independent while gaining scale. None of this is legal or financial advice, and any specific agreement deserves review by healthcare counsel before signing.
What a Management Services Organization Changes
A management services organization takes over defined administrative and operational functions, billing and revenue cycle work, human resources, vendor contracting, and compliance support, while clinical decisions stay with the physician. MGMA describes this division as the core design of an MSO arrangement, and it exists for a legal reason as much as a practical one: the corporate practice of medicine doctrine in most states keeps a lay entity from directing clinical care, so an MSO agreement has to draw a bright line between the business functions it runs and the clinical functions the practice keeps.
MGMA identifies three common ways an MSO gets paid: a flat monthly fee or a percentage of revenue where state law allows it, a cost plus model charging actual costs plus a margin, or an equity stake giving the physician ownership in the MSO itself. No standardized public benchmark publishes a typical fee percentage across these models, since terms are negotiated per agreement and vary by service scope, specialty, and state law. New York, for example, restricts revenue percentage arrangements specifically for revenue cycle management services, according to MGMA, a reminder MSO terms are state specific and worth a state law review before signing.
What an Independent Practice Association Changes
An independent practice association is the lightest touch of the three models. A practice joins primarily to aggregate for payer contracting and shared administrative services, and it keeps both its ownership and its day to day clinical operations untouched. Unlike a management services organization or a clinically integrated network, no federal agency or association publishes an official definition of what makes an arrangement an IPA specifically, so the term functions as an industry description rather than a regulated legal category, and any specific IPA agreement is worth reading closely for exactly what it does and does not require.
Because an IPA typically does not require the shared clinical protocols and quality monitoring a clinically integrated network does, it carries a lighter governance footprint, and a physician generally keeps more day to day control than under the other two models. The tradeoff is an IPA’s ability to negotiate jointly with payers rests on the same clinical integration question covered in the next section, since joint price negotiation without genuine clinical integration risks looking like price fixing rather than a lawful collaboration.
What a Clinically Integrated Network Changes
The Clinical Integration Test
A clinically integrated network exists to let otherwise independent physicians jointly negotiate payer contracts under the legal theory holding genuine clinical integration, not shared financial risk, justifies a reasonableness standard rather than automatic price fixing for the joint negotiation. MGMA describes the operative test as requiring a high degree of interdependence and cooperation among members, built on evidence based protocols, structured care review, real adherence mechanisms, and health information technology connecting the network rather than isolating each practice.
Why Non-Exclusivity Matters
MGMA flags one design feature as a core safeguard rather than an optional detail: physicians in a CIN generally need to stay free to contract independently with payers outside the network. A network requiring exclusivity looks more like collective bargaining and less like a clinically justified collaboration, exactly the distinction regulators look for.
A CIN sits alongside a related federal structure worth knowing. CMS reports 476 accountable care organizations participated in the Medicare Shared Savings Program for performance year 2024, generating a net savings to Medicare of about 2.5 billion dollars while earning about 4.1 billion dollars in performance payments to participating organizations (Source: CMS Shared Savings Program PY 2024 results). An ACO is a distinct legal structure from a CIN, but the same clinical coordination and data sharing infrastructure a practice builds for a CIN commonly supports ACO participation as well.
Value based payment is not a marginal share of the market either. MGMA data puts value based payment penetration at 44.9 percent of revenue for practices already in such an arrangement, against 28.7 percent industry wide, a gap showing practices already operating under value based models draw a larger share of their revenue through them than the average practice does.
The Regulatory Shift in 2023
HFMA reports federal antitrust regulators formally withdrew three long standing sets of guidance in 2023 previously giving healthcare provider collaborations, including IPAs, CINs, and shared savings arrangements, predictable safe harbors going back to the 1990s. The stated rationale was the healthcare environment had changed to the point the old guidance no longer fit (Source: HFMA, February 2023). The practical effect for an owner considering an IPA or CIN today is no arrangement is able to lean on a pre cleared safe harbor anymore, every collaboration gets evaluated case by case, and HFMA’s recommended response is to document the pro competitive purpose of the arrangement, put antitrust compliance protocols in place, and get healthcare counsel to review the structure specifically rather than assume a common industry pattern is automatically safe.
This is general information, not legal advice, and it is exactly the kind of decision benefiting from a healthcare antitrust attorney’s review before a practice signs onto any joint negotiation structure.
Comparing the Three Models Side by Side
| Dimension | MSO | IPN | CIN | ||||||
|---|---|---|---|---|---|---|---|---|---|
What it primarily changes | Administrative and operational functions | Payer contracting and shared services | Payer contracting through clinical coordination | ||||||
Clinical decisions | Stay with the physician by law | Stay with the physician | Certain protocols set at network level | ||||||
Typical cost structure | Service fee, cost plus, or equity stake | Membership dues, no standardized public figure | Participation cost tied to shared infrastructure | ||||||
Governance footprint | Light on clinical, heavier on business operations | Lightest of the three | Heaviest, requires shared protocols and monitoring | ||||||
Best fit | A practice wanting relief from administrative work specifically | A practice wanting contracting scale with minimal change | A practice willing to standardize care processes for negotiating strength | ||||||
Running Any of These Models on One Platform
Whichever model a practice joins, the data problem is the same. An MSO needs clean, shared reporting across every practice it supports. A CIN needs the shared clinical protocols and adherence monitoring the clinical integration test requires. HARRIS CareTracker runs multiple providers and multiple locations on one certified EHR, practice management, and billing database, so the real time reporting an MSO relies on, and the protocol adherence and quality data a CIN has to show payers, come from one connected system rather than several practices each running a different platform and reconciling the differences by hand.
For a practice weighing an IPA or CIN specifically, a platform already producing clean, comparable data across every participating physician removes one of the practical barriers to genuine clinical integration, since inconsistent documentation and reporting across member practices is a common reason a network’s clinical integration case looks weaker than intended.
A Checklist Before Joining an MSO, IPA, or CIN
Work through these before signing any affiliation agreement.
- Confirm exactly which business functions the MSO controls and which clinical decisions stay with the physician
- Get the fee structure in writing, service fee, cost plus, or equity, and confirm it complies with your state’s fee splitting law
- Ask what an IPA specifically requires versus what it merely offers, since the term carries no standardized definition
- For a CIN, confirm the shared clinical protocols and adherence monitoring are actively used rather than existing on paper only
- Confirm you keep the right to contract independently with payers outside any network you join
- Get healthcare antitrust counsel to review any joint payer negotiation structure given the 2023 regulatory shift
- Confirm your platform is able to produce the shared reporting an MSO or CIN arrangement will ask for
- Get independent financial review of any equity stake or long term services agreement before signing
Go Deeper on the Independence Decision
Related guides on the affiliation and ownership questions behind an MSO, IPA, or CIN decision.
One Platform Behind Whichever Model You Choose
HARRIS CareTracker runs multiple providers and multiple locations on a single certified EHR, practice management, and billing database, so the shared reporting an MSO needs, and the protocol adherence data a CIN has to show payers, both come from one connected system. Real time reporting on provider level productivity, contribution margin, and quality measures gives every physician in the arrangement the same clean numbers rather than reconciling different systems across different practices.
It is part of HARRIS Healthcare, owned by Constellation Software, with full HIPAA compliance. For a practice weighing an MSO, IPA, or CIN, a platform already producing consistent data across every participating provider removes one practical barrier to whichever structure the practice chooses.
Who this guide is for. This guide is for an independent primary care owner weighing a management services organization, an independent practice association, or a clinically integrated network as an alternative to selling the practice outright.
See the Platform Behind a Practice Gaining Scale on its Own Terms
Book a walkthrough of HARRIS CareTracker and see the shared reporting and quality data an MSO, IPA, or CIN arrangement runs on.
FAQs
What is the main difference between an MSO, an IPA, and a CIN?
Does joining an MSO mean giving up clinical control?
How much does an MSO typically cost?
Is an IPA the same thing as a CIN?
Why did the regulatory environment for these structures change in 2023?
Is a practice in an IPA or CIN still able to contract with payers on its own?
Is this guide legal or financial advice?
How does HARRIS CareTracker support a practice in one of these structures?
Is an accountable care organization the same thing as a CIN?
How much of practice revenue typically comes from value based payment?
Does building a CIN help a practice join a Medicare ACO too?
Is Medicare Shared Savings Program participation growing?
What Our Customers Say About Us
We chose HARRIS CareTracker for our office because of its cost-effectiveness and since changing to them, we have seen a significant increase in our monthly savings. The standout feature has been the excellent customer support and training!

Tara Warnock
Billing Specialist | Naples Vascular Specialists
It’s really easy to use HARRIS CareTracker Practice Management. Very easy to learn.

Lauren O'Brien
Billing Manager | New England OB/GYN
We have used HARRIS CareTracker in our practice for 5 years, and it has been a wonderful experience. The trainers and on-going support teams are knowledgeable, accessible, and quick to respond to queries. They provided easy-to-follow step-by-step guidance for using the software. They never failed me. I highly recommend CareTracker for practices of any size.
Linda S. Erickson
Billing Specialist | John A. Nassar, MD
Get Started Today
Connect With Us
We are here for anything you need, just drop a line and we’ll get back to you.