
Practice Revenue Cycle Management for Independent Primary Care
The revenue cycle is every step between a scheduled visit and cash in the bank. Here is how a small practice runs it well and gets paid faster.
Why Choose Us?

No Hidden Fees

No Surprise Pricing

Real Support from People Who Know Medical Billing
How to Manage the Revenue Cycle and Prevent Revenue Leakage
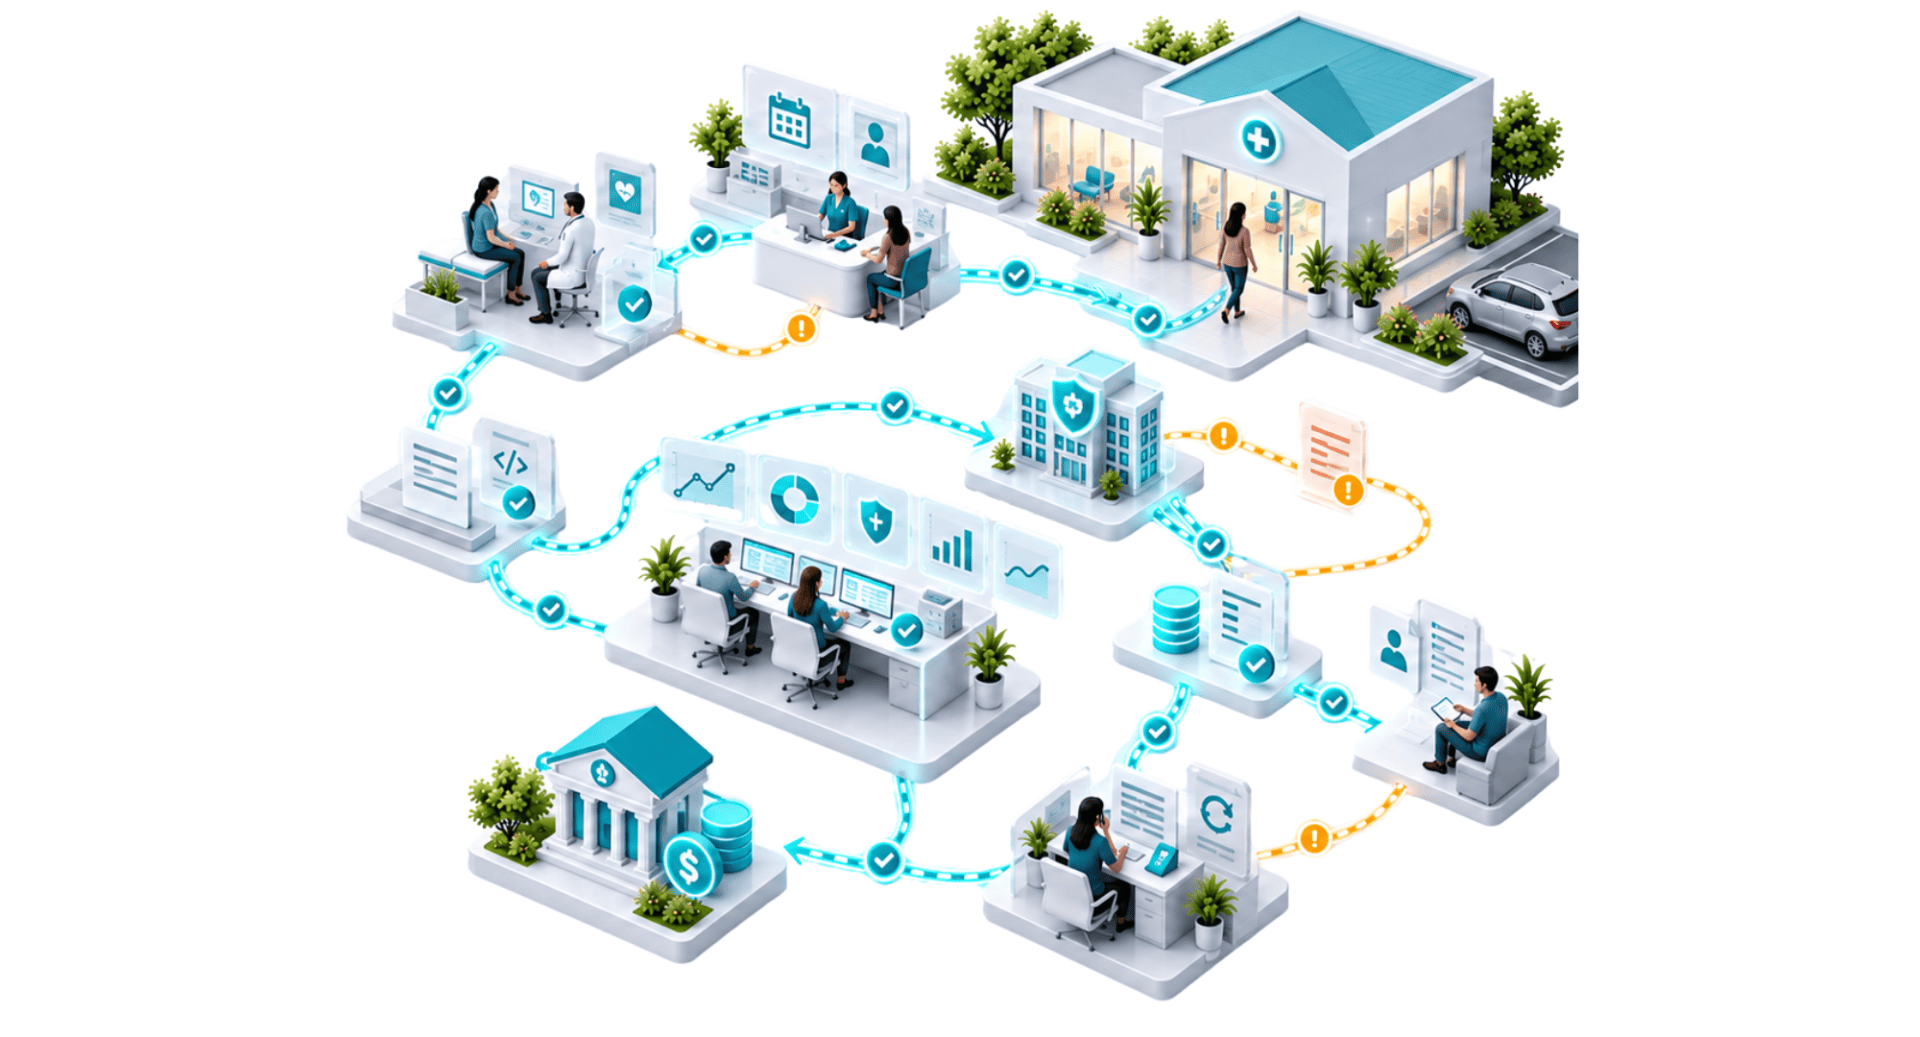
The revenue cycle is the full path a dollar travels through your practice, from the moment a patient books a visit to the moment the payment lands in your account. Eligibility checked before arrival, a visit documented and coded, a claim submitted, a payer response, patient billing for whatever is owed. A practice running this well collects most of what it earns and sees the cash within weeks. A practice running it poorly leaves real revenue sitting in denied claims, unworked accounts receivable, and patient balances nobody ever billed.
Small independent practices carry this whole cycle on a lean staff, frequently the same one or two people handling scheduling, coding, and collections. The cost of a broken step compounds because there is no back office team to catch it. A missed eligibility check becomes a denied claim weeks later, and a denied claim left unworked becomes revenue the practice never sees again. This guide covers the KPIs telling you where the cycle stands, where revenue leaks out, and the fixes a small team puts in place without adding headcount.
The Revenue Cycle, Step by Step
Six steps carry a claim from scheduled visit to paid balance: eligibility verification before the appointment, accurate registration at check in, clinical documentation and coding of the visit, claim submission to the payer, payer adjudication and payment posting, and patient billing for the remaining balance. A weak link anywhere in this chain shows up downstream as a denial, a slow payment, or an uncollected balance.
For a small practice, the payoff of treating the cycle as one connected process rather than five separate tasks is real. Eligibility and coding are not billing department problems, they are revenue cycle problems starting at the front desk and the exam room. HARRIS CareTracker runs registration, documentation, claims, and collections on one database, so a change made at check in shows up in the claim rather than getting lost between disconnected systems.
The KPIs Telling You Where You Stand
A handful of numbers tell a practice whether the revenue cycle is healthy. Days in accounts receivable measures how long it takes to get paid after a visit, and HFMA defines it as a standard revenue cycle metric worth tracking against your own trend over time. The clean claim rate measures the share of claims paid on first submission without a rework cycle, and the net collection rate measures what a practice collects against what it is contractually owed, the truest measure of revenue capture.
Watch the trend, not a single month. A practice tracking days in accounts receivable, clean claim rate, denial rate, and cost to collect on a monthly cadence catches a slipping metric while it is still small. One only watching the bank balance finds out about a broken step months later, after unpaid claims stack up past the point of an easy fix. HARRIS CareTracker’s reporting surfaces these numbers in real time, so an owner sees the trend without waiting on a manual report.
Put a number on each metric rather than tracking it loosely. HFMA benchmarks a healthy net collection rate above 95 percent, a clean claim rate above 95 percent, and days in accounts receivable under 30 to 40, with an initial denial rate under 5 percent against an industry average near 12 percent. A practice falling short on any one of these has a specific problem to fix, not a vague feeling something is off.
Where the Revenue Leaks Out
Eligibility and Prior Authorization
A manual eligibility check costs a practice about 12.95 dollars in staff time against 2.04 dollars for an electronic check, according to the CAQH Index, and the gap on prior authorization is wider still: 16.29 dollars manual against 5.43 dollars electronic, with a manual request taking about 24 minutes of staff time. Multiply either figure across a full patient panel and the manual approach is where a lean front desk loses hours it does not hold.
Prior authorization carries a second cost beyond staff time. In an American Medical Association survey, physicians report completing an average of 40 prior authorizations a week, consuming roughly 13 hours of physician and staff time, and nearly a third say requests are regularly denied outright (Source: AMA 2025 Prior Authorization Physician Survey). Automating eligibility and flagging authorization requirements before the visit is one of the highest return fixes a small practice makes to its revenue cycle.
Claims and Denials
About 12 percent of medical claims are denied before ever reaching payment, per the CAQH Index, and MGMA has tracked a single specialty first submission denial rate near 8 percent, a figure holding roughly steady for years even as the volume of denials climbs. A denied claim is not a lost claim if it gets reworked and resubmitted, but a small practice without a denial workflow lets a real share sit unworked, turning a fixable delay into revenue the practice never recovers.
The fix starts before submission. Claim scrubbing against payer edit rules catches the errors causing a first round of denials, coding accuracy prevents a second wave, and a standing workflow for the claims still denied keeps the appeal window from closing unused. HARRIS CareTracker scrubs claims against current edits before they leave the practice and flags high risk claims for review, so fewer denials happen in the first place.
The opportunity is not small industry wide. The CAQH Index puts the remaining savings available from moving manual administrative transactions to electronic ones at more than 20 billion dollars a year across the medical industry (Source: 2025 CAQH Index Report, DataSpring), most of it sitting in exactly the eligibility, prior authorization, and claim status transactions covered above. A single small practice captures its own proportional slice of this by automating the same transactions.
Collecting What Patients Owe
Patient responsibility is a growing share of practice revenue as deductibles and copays climb, and it is the piece of the revenue cycle most likely to fall through the cracks in a small office. Collecting at the point of service, giving patients a clear estimate before the visit, and running a portal where a balance is paid online without a phone call, all raise the share of patient balances a practice collects rather than writes off.
Digital tools help here more than a phone call. ONC data on patient portal use shows when a provider actively encourages portal use, 87 percent of patients access it, against 57 percent among those not encouraged (Source: ONC Data Brief 77), a gap the front desk controls directly. A practice pointing patients to a portal for statements and online payment collects faster and spends less staff time chasing a balance by phone.
Running a Revenue Cycle a Small Team Manages With Ease
None of this needs a large billing department. It needs a platform where eligibility, coding, claims, and collections run as one connected workflow rather than five disconnected steps a lean team stitches together by hand. Automated eligibility and claim scrubbing prevent the errors creating denials, real time reporting surfaces a slipping metric early, and a patient portal moves collections online where a small staff is not spending its day on the phone.
HARRIS CareTracker puts the certified EHR, practice management, and medical billing on a single database built for exactly this kind of lean operation, so a one to ten provider practice runs a revenue cycle otherwise needing a dedicated billing team. Documentation flows into a clean claim without re keying, eligibility is checked automatically before the visit, and reporting shows the whole cycle from one login.
A Practice Revenue Cycle Health Checklist
Run through these to find where your practice is leaving revenue on the table.
- Verify eligibility electronically before every visit, not at check in
- Flag prior authorization requirements before the appointment
- Track days in accounts receivable, clean claim rate, and net collection rate monthly
- Scrub claims against payer edits before submission
- Work every denial within the appeal window rather than writing it off
- Collect estimated patient responsibility at the point of service
- Give patients a portal to view statements and pay online
- Review the revenue cycle trend monthly, not only the bank balance
Go Deeper on the Revenue Cycle
Related guides on the pieces making up a healthy revenue cycle.
- Adding a Provider or Opening a Second Location
- Front Office Efficiency for Small Practices
- How to Reduce Claim Denials
- EHR and Practice Management for Primary Care
- MSO vs IPA vs CIN
- Chronic Care Management recurring revenue
- Private equity acquisition of medical practice
- Negotiate payer contracts independent practice
A Revenue Cycle Built Into the Platform
HARRIS CareTracker runs eligibility verification, claim scrubbing, coding support, and patient collections on the same database as the clinical record, so the revenue cycle is not a separate system a lean staff manages by hand Eligibility is checked automatically before the visit, claims are scrubbed against current edits before they leave the practice, and real time reporting shows days in accounts receivable, denial rate, and collections in one place.
It is part of HARRIS Healthcare, owned by Constellation Software, with full HIPAA compliance. For an independent practice without a dedicated billing department, the payoff is a revenue cycle running on automation rather than staff time, so the same one or two people carrying scheduling and billing today keep pace with a growing panel without adding headcount.
Who this guide is for. This guide is for an independent primary care owner or administrator wanting to see and improve every step between a scheduled visit and cash in the bank.
See a Revenue Cycle a Lean Team Runs with Ease
Book a walkthrough of HARRIS CareTracker and see how automated eligibility, claim scrubbing, and real time reporting run your revenue cycle for you.
FAQs
What is revenue cycle management for a medical practice?
What KPIs should a small practice track for revenue cycle health?
Where does revenue typically leak out of a small practice?
How much does a manual eligibility check cost compared to an electronic one?
How do I reduce denied claims in my practice?
How do I get patients to pay their balance faster?
Does a small practice need a billing department to run a healthy revenue cycle?
How does HARRIS CareTracker help with revenue cycle management?
What is a healthy net collection rate for a primary care practice?
How large is the industry wide savings opportunity from automating billing transactions?
What counts as a good clean claim rate?
How frequently should a practice review its revenue cycle numbers?
What Our Customers Say About Us
We chose HARRIS CareTracker for our office because of its cost-effectiveness and since changing to them, we have seen a significant increase in our monthly savings. The standout feature has been the excellent customer support and training!

Tara Warnock
Billing Specialist | Naples Vascular Specialists
It’s really easy to use HARRIS CareTracker Practice Management. Very easy to learn.

Lauren O'Brien
Billing Manager | New England OB/GYN
We have used HARRIS CareTracker in our practice for 5 years, and it has been a wonderful experience. The trainers and on-going support teams are knowledgeable, accessible, and quick to respond to queries. They provided easy-to-follow step-by-step guidance for using the software. They never failed me. I highly recommend CareTracker for practices of any size.
Linda S. Erickson
Billing Specialist | John A. Nassar, MD
Get Started Today
Connect With Us
We are here for anything you need, just drop a line and we’ll get back to you.