
How to Reduce Claim Denials in a Primary Care Practice
A denied claim is not lost revenue if it gets caught and fixed. Here is where denials come from and how a small practice prevents and recovers them.
Why Choose Us?

No Hidden Fees

No Surprise Pricing

Real Support from People Who Know Medical Billing
Reduce Medical Claim Denials and Protect Practice Revenue
About 12 percent of medical claims are denied before payment, according to the CAQH Index, and MGMA reports 60 percent of medical group leaders saw denial rates rise in a year over year comparison. For a large hospital system, a denial team reworks the backlog. For an independent primary care practice, the same denial rate falls on a front desk and a biller already stretched thin, and the revenue sits unpaid until somebody finds time to fix it.
Denials are not random. The reasons repeat across practices, MGMA points to insufficient clinical documentation, patient eligibility and registration errors, untimely filing, and incorrect modifier use as the recurring drivers, and each has a known fix. This guide covers why claims get denied, how to stop the preventable ones before submission, and how to build a workflow recovering the ones still slipping through.
Why Claims Get Denied
Registration and eligibility errors are the most common denial cause a small practice sees, a patient’s coverage lapsed, the wrong plan was on file, or an authorization was never confirmed before the visit. MGMA’s research also names untimely filing and incorrect modifier use, particularly modifier 25 on evaluation and management visits, among the recurring drivers, along with documentation gaps leaving a coder unable to support the billed code.
Prior authorization is its own denial source. In an American Medical Association survey, nearly a third of physicians report authorization requests are regularly or always denied, and 95 percent say the process delays care patients need (Source: AMA 2025 Prior Authorization Physician Survey). A denial tied to a missing or expired authorization is almost always preventable if the requirement is caught before the visit rather than after the claim comes back.
Denials do not fall evenly. A 2024 study in JAMA Network Open found preventive care claims were denied at higher rates for patients in lower income areas and for Black and Hispanic patients specifically (Source: Hoagland et al., JAMA Network Open, 2024), evidence a denial problem is also an equity problem inside a practice’s own patient panel. Reviewing denial patterns by service type and by patient population, not only by payer, surfaces a disparity a reason code alone will not show.
Prevent the Denials You See Coming

Verify Eligibility and Authorization Before the Visit
Run eligibility electronically before every appointment, not at check in, so a lapsed plan or a change in coverage surfaces while there is still time to fix it. Confirm any authorization requirement at the same step. The CAQH Index shows electronic eligibility checks run about 2.04 dollars against 12.95 dollars for a manual check, so automating this step also frees the staff time a denial workflow needs later.

Scrub Every Claim Before It Leaves the Practice
Claim scrubbing checks a claim against payer specific edit rules before submission, catching coding mismatches, missing modifiers, and documentation gaps a coder would otherwise only find after a denial comes back. HARRIS CareTracker scrubs claims against current edits automatically and flags high risk claims for review, so the errors driving a first round of denials get caught before submission rather than three weeks later.
Build a Workflow for the Denials Still Happening
Even a well run practice sees a few denials, and the difference between recovered revenue and a write off is whether somebody works the claim inside the appeal window. Assign denial follow up to a specific person or a specific block of time each week, rather than leaving it to whoever has a spare moment, and track denials by reason code so a repeating cause gets fixed at the source rather than reworked every time it recurs.
Timely filing matters here. Medicare requires claims filed within twelve months of the date of service, and commercial payers set their own, frequently shorter, windows, so a denial sitting in a queue past the filing deadline becomes unrecoverable. A standing weekly review of the denial queue, sorted by how close each claim is to its filing deadline, keeps the clock from running out on revenue a practice is still entitled to collect.
Track the Number Telling You If It Is Working
The first submission denial rate is the number to watch, MGMA has tracked single specialty practices near an 8 percent aggregate for several years, so a practice above this figure is losing more revenue to rework than it should be. Track the rate monthly, and break it down by reason code, because a single recurring cause, say eligibility errors from one payer, is regularly responsible for a large share of the total and is the fastest one to fix.
A falling denial rate compounds. Fewer denials means less staff time spent reworking claims, faster payment, and a lower cost to collect across the whole revenue cycle. HARRIS CareTracker’s reporting breaks denials down by reason and payer automatically, so a practice sees the pattern without pulling the data by hand.
Rework carries its own price tag. MGMA estimates the average cost to rework a single denied claim at 25.20 dollars in staff time, before counting the revenue at risk if the claim is never resubmitted. Multiplied across even a modest monthly denial volume, the rework cost alone justifies front end prevention over an after the fact fix.
A Denial Prevention Checklist
Work through these to stop preventable denials and recover the ones still happening.
- Verify eligibility and authorization electronically before every visit
- Scrub every claim against payer edits before submission
- Confirm modifier use and documentation support the billed code
- Assign denial follow up to a specific person or weekly block of time
- Track denials by reason code, not only by total count
- Sort the denial queue by how close each claim is to its filing deadline
- Track the first submission denial rate monthly against the 8 percent benchmark
- Fix the root cause behind a repeating denial reason rather than reworking it every time
Go Deeper on the Revenue Cycle
Related guides on the pieces making up a healthy revenue cycle.
Denial Prevention Built Into the Claim Workflow
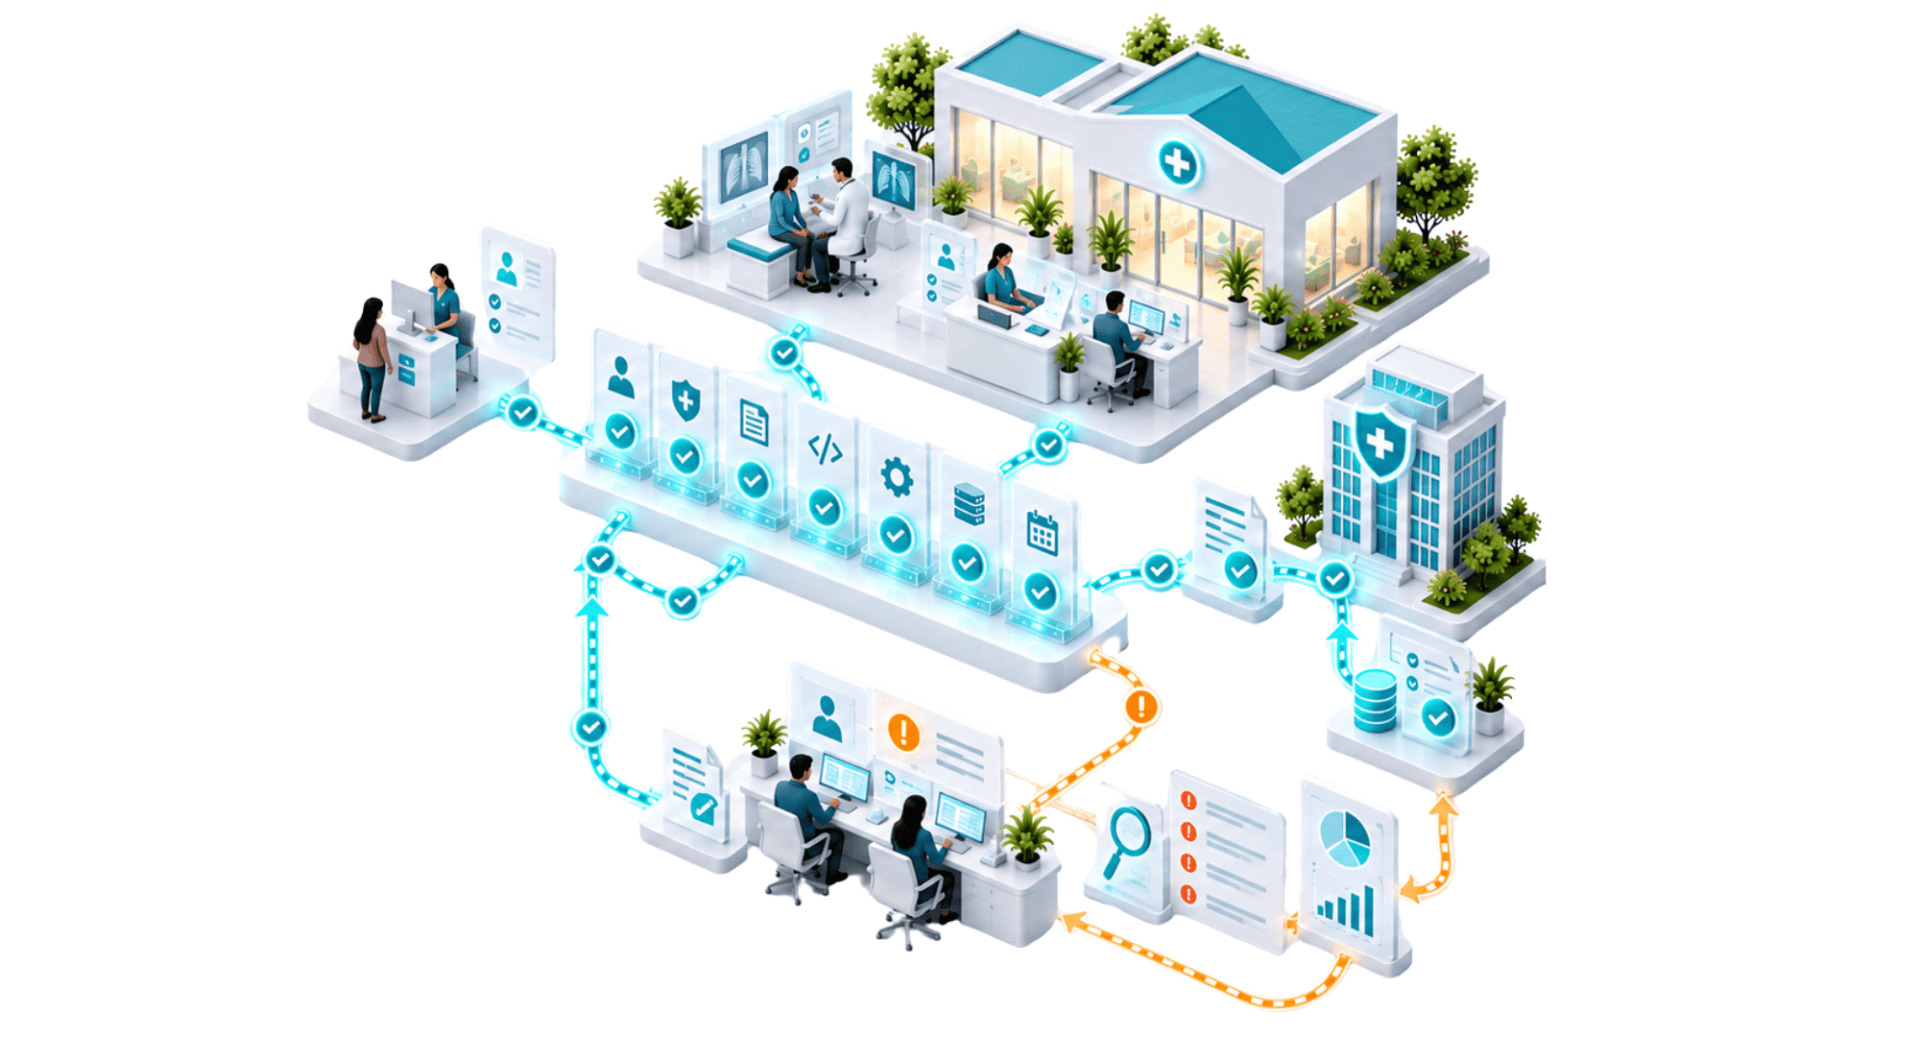
HARRIS CareTracker checks eligibility automatically before the visit, scrubs claims against current payer edits before submission, and flags high risk claims for review, so the errors causing most denials get caught before a claim ever leaves the practice. Reporting breaks denials down by reason code and payer, so a repeating cause is visible and fixable rather than buried in a spreadsheet.
It is part of HARRIS Healthcare, owned by Constellation Software, with full HIPAA compliance. For a small practice without a dedicated denial team, the result is fewer denials to begin with and a clear queue for the ones still happening, so revenue does not quietly disappear into an unworked claim.
Who this guide is for. This guide is for an independent primary care owner, administrator, or biller trying to lower a rising denial rate and recover revenue sitting in unworked claims.
See Denial Prevention Built into your Workflow
Book a walkthrough of HARRIS CareTracker and see how automated eligibility checks and claim scrubbing catch denials before they cost you revenue.
FAQs
What is the average claim denial rate for a medical practice?
What are the most common reasons claims get denied?
How do I prevent claim denials before they happen?
What should I do with a claim already denied?
What is the appeal window for a denied Medicare claim?
How do I know if my denial rate is a problem?
Does automating eligibility checks reduce denials?
How does HARRIS CareTracker help reduce denials?
Do claim denials fall evenly across patients?
What does it cost to rework a denied claim?
Should a small practice review denials by patient demographic and by payer?
Is the cost of reworking a claim worth counting alongside the denial rate?
What Our Customers Say About Us
We chose HARRIS CareTracker for our office because of its cost-effectiveness and since changing to them, we have seen a significant increase in our monthly savings. The standout feature has been the excellent customer support and training!

Tara Warnock
Billing Specialist | Naples Vascular Specialists
It’s really easy to use HARRIS CareTracker Practice Management. Very easy to learn.

Lauren O'Brien
Billing Manager | New England OB/GYN
We have used HARRIS CareTracker in our practice for 5 years, and it has been a wonderful experience. The trainers and on-going support teams are knowledgeable, accessible, and quick to respond to queries. They provided easy-to-follow step-by-step guidance for using the software. They never failed me. I highly recommend CareTracker for practices of any size.
Linda S. Erickson
Billing Specialist | John A. Nassar, MD
Get Started Today
Connect With Us
We are here for anything you need, just drop a line and we’ll get back to you.