
I meet plenty of physicians who are terrified of upcoding. They worry about payer audits, recoupments, and the prospect of defending their documentation to a reviewer who never met the patient.
So they do what seems like the safe thing. They bill a lower level.
Here is the problem. That decision can cost a practice thousands of dollars per provider every year, and coding lower than the documentation supports is not the same thing as coding correctly. Coding less is not the same as coding correctly. That one idea is the whole post.
Dr. Whitley had practiced pediatrics in Cookeville for twenty six years when I met him. He knew most of his patients’ grandparents and wrote notes as thorough as any I ever read. I spent a morning shadowing him, and at lunch I told him what I noticed. His notes described complex visits, and his claims billed simple ones. Nobody in the practice had ever put the two side by side. Once his nurse started recording the history in templates he reviewed and signed, and the coding matched what he documented, average reimbursement per visit rose about 11 percent, with nothing billed that the note did not support.
Physicians who pick their own visit levels are usually not trying to maximize reimbursement. They are trying to stay out of trouble. I understand the concern. Nobody wants an audit letter. But conservative coding turns into a habit fast, above all when nobody checks whether the codes match the work being documented.
Why providers undercode
Nobody wants to be accused of upcoding. Physicians hear stories about payer audits and repayment demands, and a share of them decide it is easier to bill a 99213 than risk explaining a 99214. I understand the thinking. But picking a lower code on purpose is no substitute for understanding the documentation requirements.
Then there is plain old habit. A physician gets comfortable billing 99213 for routine follow up visits. Five years later, the patient panel is older, more patients carry several chronic conditions, and the medical decision making is more complicated. The physician still reaches for the same code, because it is familiar, whether or not it is correct.
Fear and habit are not the only causes. Training gaps play a part, since plenty of providers learned E/M coding under older rules. Office visit levels are now selected based on medical decision making or total time on the date of the encounter, and a provider who is unsure how to apply either one will default to the level they know. Workflow matters too. Templates that make it easy to document a simple visit and hard to document a complex one push the note, and the code, toward the low end.
It helps to separate two different problems. Sometimes the documentation is incomplete, so the note supports a lower level than the visit deserved. Other times the documentation is complete and the provider still selects a lower level. The first is a documentation problem. The second is a coding problem. They need different fixes.
The math
Here are hypothetical numbers to show how fast this adds up.
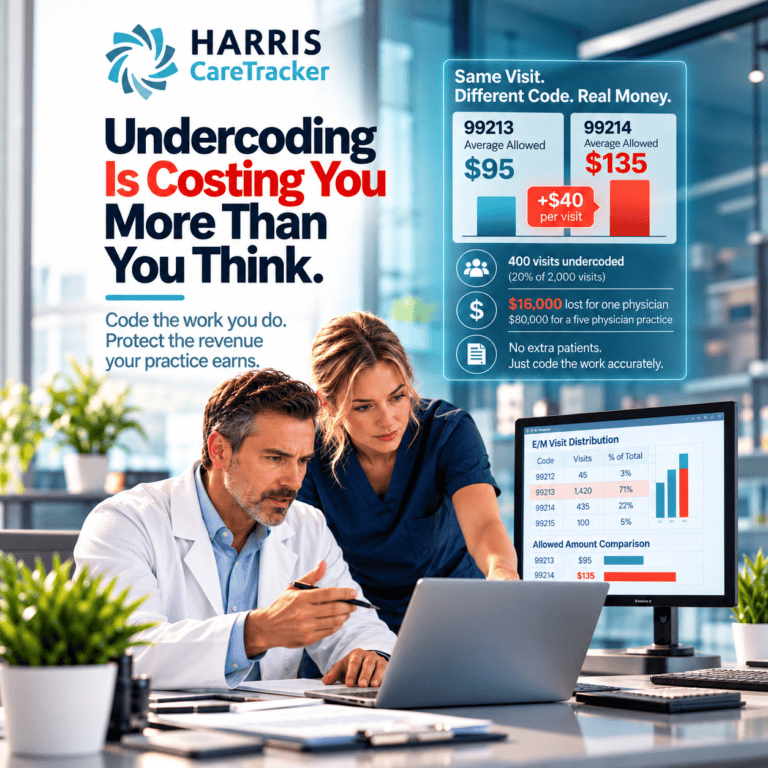
Suppose your average allowed amount for a 99213 is $95 and your average allowed amount for a 99214 is $135. That is a $40 difference.
Now assume a physician bills 2,000 visits a year as 99213, and a coding review finds that 20 percent of those visits had documentation supporting a 99214. That is 400 visits billed below the supported level.
At $40 a visit, the difference is $16,000 for one physician. Across a five physician practice, the hypothetical total is $80,000 a year.
Nobody had to see another patient. Nobody had to work another Saturday. The practice only needed to code the work accurately.
These figures are illustrative, not verified Medicare or commercial rates. Your results depend on your payer contracts, your documentation, the coding rules, and the number of encounters that support the higher level. Run the same math with your own allowed amounts and your own review findings.
How to spot it
How to spot it
Start with your E/M level distribution. Pull every return patient office visit for the last 12 months, by provider, and count the visits billed at each level from 99212 through 99215.
Once the numbers are in front of you, compare them. If two physicians in the same specialty see comparable patients, and one bills almost everything as a 99213 while the other shows a much broader spread, I would want to know why.
That does not automatically mean anyone is coding incorrectly. Their patients may be different. Their documentation may be different. But it is a good reason to pull a sample of charts and take a closer look.
When nearly every return visit lands at the same level, I start asking questions. The distribution may accurately reflect the patients. Or the physician may be choosing the same code without fully weighing the medical decision making. A utilization report alone cannot answer that question. You need to look at the documentation.
Undercoding is a compliance issue too
Here is something I wish more physicians understood. Coding conservatively and coding accurately are two different things.
If the documentation supports a 99214, picking a 99213 because you are afraid of an audit does not make the documentation stronger or the coding more defensible. It makes the claim wrong in the other direction.
The goal is not to bill the highest level possible. It is not to bill the lowest level possible, either. The goal is to bill the level the documentation and the applicable coding rules support.
Fixing it
Please do not solve this by making every physician sit through another two hour coding presentation.
Pull five of their own charts. Sit down with the provider and a qualified coder. Show them where the documentation supports the selected level and where it does not. Physicians are busy. They do not need a lecture on the entire coding manual. They need specific examples from their own encounters that show what to document, what to code, and why.
Then make review routine. I would rather see a practice review 10 charts per physician every quarter than run one big audit every three years. Ten charts is a routine check, not a statistically valid sample of the whole practice, and that is fine for this purpose. The point is not to catch physicians doing something wrong. It is to make accurate coding part of the normal workflow.
And when the review shows a physician is coding correctly, tell them. Confidence matters, and providers who spent years worrying about whether their coding would survive an audit need to hear it.
How HARRIS CareTracker helps
We tend to underestimate what happens when documentation gets pushed to the end of the day. A physician sees 25 patients, handles phone calls, answers messages, and finally sits down at 9:00 that night to finish notes. By then, most of the detail from the 9:30 patient that morning is gone.
This is one area where technology can help. AMPLIFY, the ambient listening assistant from HARRIS CareTracker, records the patient encounter conversation and helps organize it into a structured clinical note for the provider to review and sign.
It does not replace the physician’s judgment, and it does not decide what code gets billed. Medical decision making can depend on work that never gets said out loud in the room. What AMPLIFY does is help the provider produce a more complete note without relying on memory hours after the appointment. More complete documentation gives the provider and the coding team a firmer foundation for selecting the right E/M level.
Here is a question worth asking your billing manager this week: what share of our return patient visits are billed as 99213? Then ask a second one: when did anyone last check whether the documentation supported those levels?
If the answer is “I don’t know,” you found a good place to start. Your physicians may be coding perfectly. Or your practice may be giving away money every year because everyone thought billing less was the safe choice.
Follow for more on revenue cycle management, medical billing workflow, and coding practices that protect your net collection rate and clean claim rate.
Frequently Asked Questions
What is undercoding in medical billing?
Is undercoding a compliance risk?
How do I know if my providers are undercoding?
Is undercoding a documentation problem or a coding problem?
Does ambient documentation pick the E/M level?
About the Author
Thomas Koehl is a 30 year health technology veteran and currently Director of Marketing at Harris CareTracker. Prior leadership roles at QRS Healthcare Solutions focused on supporting revenue cycle management partners. Following Hurricane Katrina, he served as Director of a large New Orleans medical clinic that delivered care to over 32,000 patients. Koehl has testified before the U.S. House Committee on Energy and Commerce as an expert witness on disaster healthcare delivery. He also volunteers as COO of International Medical Alliance, a nonprofit providing free medical care to impoverished communities in developing countries. He writes about the business, strategy, and human side of health technology for the practitioners and leaders living it day to day.
Follow me here for more breakdowns, and follow HARRIS CareTracker for product updates and resources.


