
Practice managers tell me they would rather put up with five more years of bad software than risk disrupting their cash flow for five weeks.
I understand the concern. With payroll coming up, bills to pay, and physicians expecting their distributions, the last thing anyone wants is a software conversion that interrupts collections. But staying on software that costs you money every month carries its own financial risk.
In 2015 a billing company owner in central Kentucky named Diane kept a calendar on her office wall with October 1 circled in red. Someone on her staff had written “ICD10 DOOMSDAY” under it. She had reason to worry. During the 5010 transition in 2012, her cash flow fell almost 40 percent for two months while payers rejected claims her team did not understand. So we started in May. Her team dual coded a sample of claims every week, sent end to end test files to the major Kentucky payers in June, rebuilt every client’s charge templates over the summer, and she drew on her line of credit in September and set the money aside. On October 1 her clean claim rate held at 95 percent, payments arrived on schedule, and she paid the line of credit back in December without touching it.
Diane’s 2012 experience and her 2015 experience used the same staff and the same clients. The second one went smoothly because of everything her team did before the date arrived. Software conversions work the same way. I watched conversions go so smoothly the physicians barely noticed, and I watched practices spend months recovering from a poorly managed one. When a conversion goes badly, the cause is almost always something the practice skipped before launch day.
Four ways a software conversion can wreck your collections
Payer enrollment and EDI gaps. EDI is the electronic connection that carries claims and payments between your system and each payer. Here is a problem that catches practices completely off guard. The new software is installed. Everyone is trained. The first claims are ready to go. Then someone finds out a major payer never finished processing the enrollment paperwork for the new system. The software works fine, and the claims still are not going anywhere.
Clearinghouse setup delays. Testing, trading partner agreements, and payer ID mapping all take time. A clearinghouse connection nobody tested before launch tends to fail on the first batch.
The staff learning curve. Do not underestimate what happens when you take an experienced biller who spent ten years in one system and put an unfamiliar screen in front of them. They know how to do their job. They do not know how to do it in the new software yet. Everything takes longer. Charges stack up. Claims go out late, and the frustration builds.
Old A/R that nobody works. A/R is the money payers and patients still owe you for services already delivered, and this is the one I worry about most. On launch day, something predictable happens: everyone focuses on the new software. Say there is $200,000 in outstanding receivables still sitting in the old system. Those claims do not resolve themselves. Someone still has to work the denials, follow up with payers, and post the payments. I watched practices put enormous effort into new technology while paying almost no attention to the money they already earned. That is an expensive oversight.
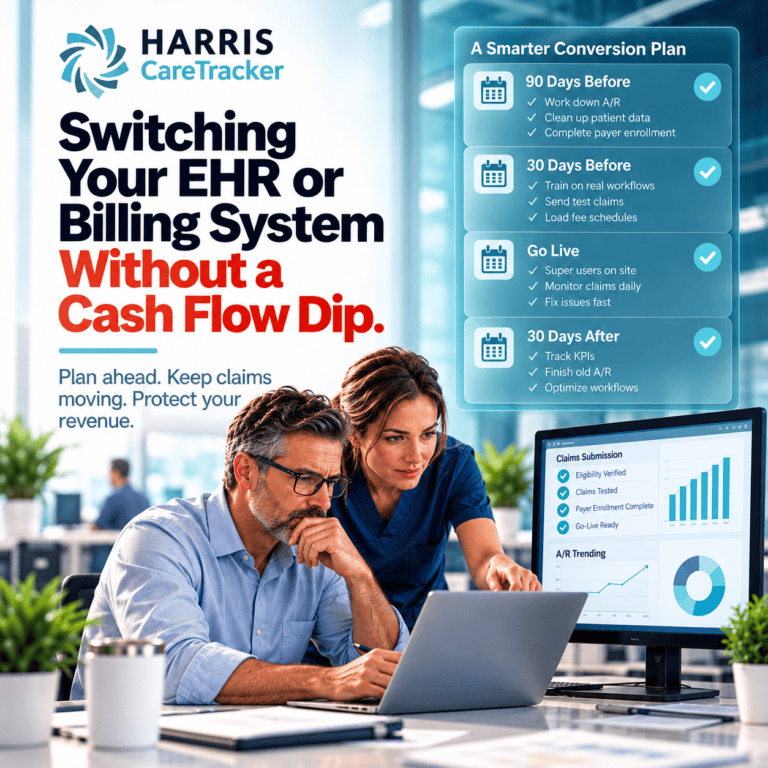
90 days before launch
The work needs to start long before launch. Ninety days is a useful planning target, though the real timeline depends on your practice, your payers, and the complexity of the conversion. Before anyone worries about new dashboards, I would focus on three things.
Work down the A/R in the old system while your staff still know it well. Every denial worked now is one less claim to protect during the transition.
Clean up patient demographics so bad data does not migrate. Duplicate patients, outdated insurance, and wrong addresses cause denials in a new system the same way they did in the old one.
Get every payer enrollment and EDI connection ready, and give one person ownership of that list. Start the paperwork now, because certain payer enrollments take weeks.
30 days before launch
I was never a fan of software training where someone clicks through 50 screens while the staff watches.
Show me how to register a patient. Show me how to fix a rejected claim. Show me how to post an insurance payment that does not match what we expected. That is training. Everything else is a product demonstration.
Send test claims for your major payers and make sure they are accepted. A rejected test claim costs nothing. A rejected batch of real claims after launch costs days. Load your fee schedules and check that each CPT code prices the way it did in the old system.
Cutover
Here is one piece of advice I give every practice preparing for a conversion: do not shut the door on the old billing system because the new one is running.
Your old system still has a job to do. Every outstanding claim needs an owner, and someone needs to keep working those accounts until they are resolved. Meanwhile, all new charges go into the new system. Two systems, two defined jobs, and nobody wondering who owns the old claims.
90 days after launch
Do not panic if days in A/R creeps up during the first few weeks. A little disruption is normal while people learn new workflows. But do not ignore a number that keeps moving in the wrong direction, either.
Watch five numbers every week for the first 90 days: cash receipts, claim submission volume, days in A/R, clean claim rate (the share of claims accepted and paid without correction), and first pass rate (the share of claims paid on the first submission with no follow up). Vendors define those last two differently, so pick one definition and use it the whole time.
Cash receipts and claim volume are the two that tell you first. If either one drops and stays down, find out why right away. Waiting until the end of the month to look can turn a manageable problem into a serious one. Name one person who owns these numbers after launch and reports on them weekly.
Where HARRIS CareTracker fits
The technology is only part of a conversion. You also need people who understand what happens financially when the transition goes wrong, which is why I put so much weight on implementation support.
At HARRIS CareTracker, our implementation and customer success teams work with practices through the transition, including data migration, payer setup, training, and the first weeks on the new system. Getting the software running is part of that work. Keeping the practice operating and collecting while the change happens is the larger part. And with practice management, EHR, and billing on one platform, the practice goes through one transition rather than three.
If your practice is still on software that frustrates your staff, slows down billing, or makes it hard to tell where your money is going, fear of switching should not be the only reason you stay. A conversion carries risk. So does spending five more years working around a system you outgrew. What matters is whether your plan can carry the risk of the switch.
For those of you who went through an EHR or billing software conversion: what caused the biggest headache?
Frequently Asked Questions
How long does an EHR or billing system switch take?
How do I protect cash flow during a system switch?
What happens to A/R in the old system?
Should a practice run two systems at once?
Which metrics should I watch after launch?
About the Author
Thomas Koehl is a 30 year health technology veteran and currently Director of Marketing at Harris CareTracker. Prior leadership roles at QRS Healthcare Solutions focused on supporting revenue cycle management partners. Following Hurricane Katrina, he served as Director of a large New Orleans medical clinic that delivered care to over 32,000 patients. Koehl has testified before the U.S. House Committee on Energy and Commerce as an expert witness on disaster healthcare delivery. He also volunteers as COO of International Medical Alliance, a nonprofit providing free medical care to impoverished communities in developing countries. He writes about the business, strategy, and human side of health technology for the practitioners and leaders living it day to day.
Follow me here for more breakdowns, and follow HARRIS CareTracker for product updates and resources.


